L564 Form Printable
L564 Form Printable - This form is your application for medicare part b (medical insurance). 202 rows if you can't find the form you need, or you need help completing a form, please call. You can use this form to. You can complete the part b sep online or you can mail your completed cms. Ask your employer to fill out section b. Send the completed form to your local social. Fill out section a and take the form to your employer. 5 star ratedmoney back guarantee30 day free trialfast, easy & secure You need to get the completed form from your employer and include it with your application for. Department of health and human services.
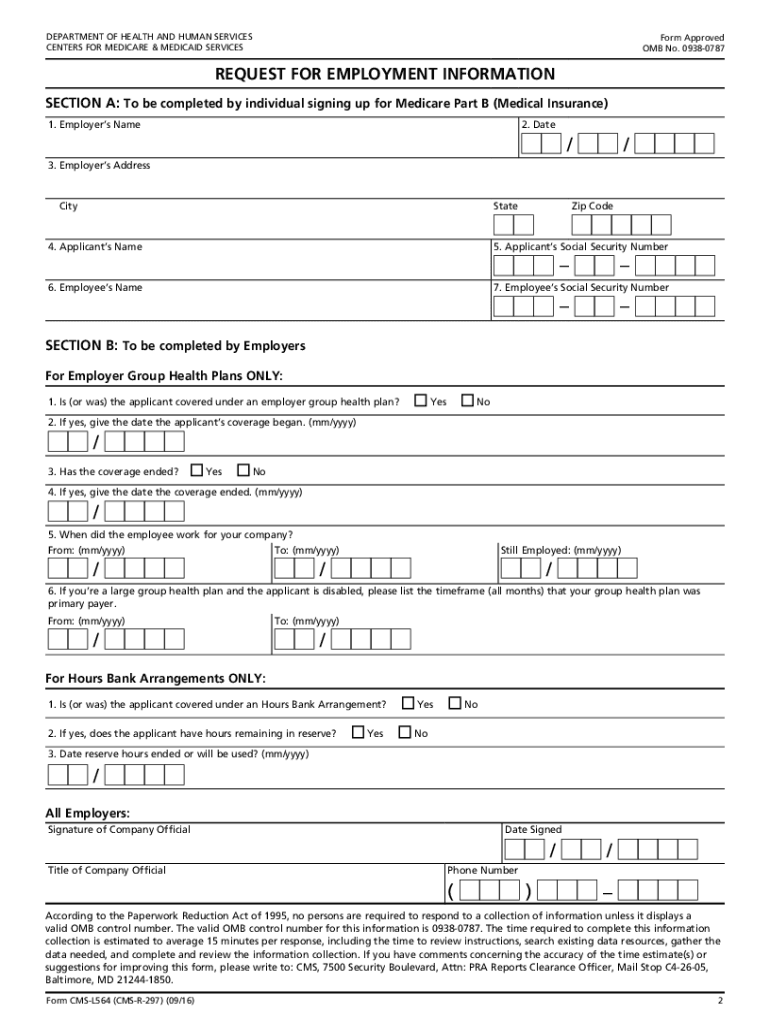
20162021 Form CMSL564 Fill Online, Printable, Fillable, Blank pdfFiller
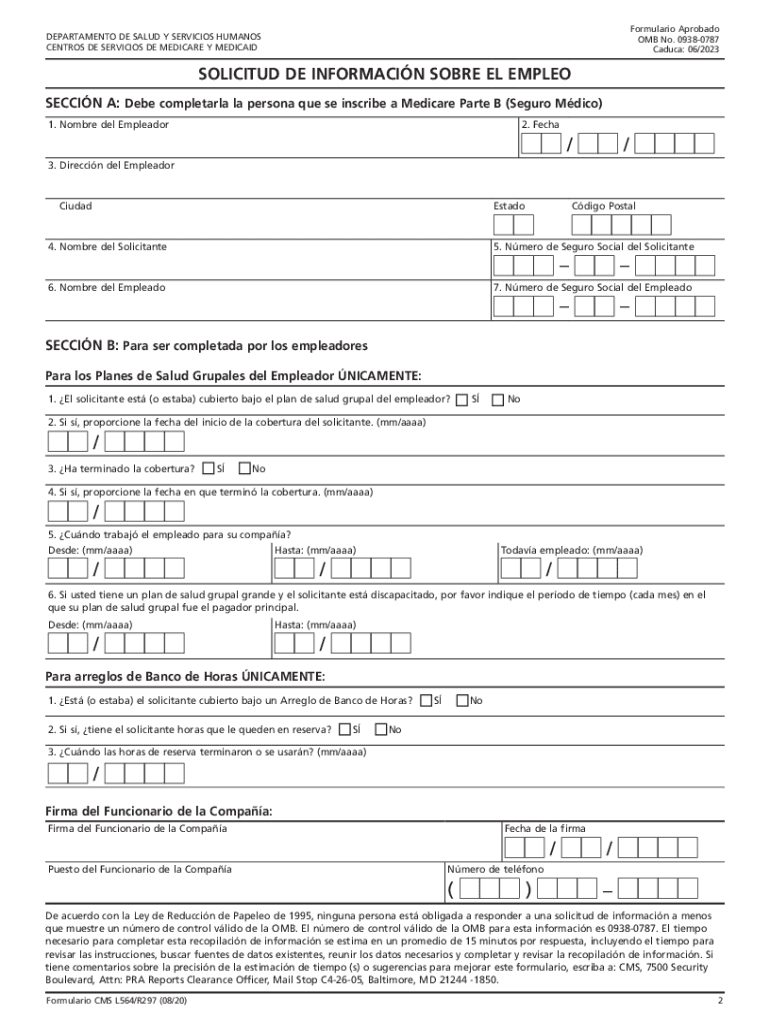
Printable Form Cms L564 Cms R 297 Printable Forms Free Online

Fillable Online CMSL564 Request for Employment

Form CmsL564 Request For Employment Information printable pdf download
Printable Medicare Abn Form 2022 Customize and Print

Form CMSL564

Form CMS L564 / R297 template

Fillable Online Forms OPM.govInstructions for Petition for

Form CMS L564 Download Fillable PDF or Fill Online Request for

Basic Employment Application Pdf
You Need To Get The Completed Form From Your Employer And Include It With Your Application For.
Fill out section a and take the form to your employer. You can complete the part b sep online or you can mail your completed cms. 202 rows if you can't find the form you need, or you need help completing a form, please call. Department of health and human services.
This Form Is Used To Prove Your Group Health Care Coverage Based On Current Employment.
You can use this form to. Send the completed form to your local social. Ask your employer to fill out section b. Download and print this form to prove your group health care coverage based on current.
This Form Is Your Application For Medicare Part B (Medical Insurance).
5 star ratedmoney back guarantee30 day free trialfast, easy & secure