Hipaa Form Printable
Hipaa Form Printable - How to fill out a hipaa release form. In the event the health information described below includes any of these types of information, and i initial the line on the box in item 8(a), i specifically authorize release of such information to the person(s) indicated in item 7. If any sections are left blank, this form will be invalid and it will not be possible for your health information to be shared as requested. Powers granted under a medical release can be revoked or reassigned at any time. I understand that by signing this consent i authorize you to use and disclose my protected health information to carry out: Direct free access to pdf of hipaa release. This form is for use when such authorization is required and complies with the health insurance portability and accountability act of 1996 (hipaa) privacy standards. The medical record information release (hipaa) form allows patients to give authorization to a 3rd party and access their health records. Medical release forms include details about the information authorized for disclosure, its purpose, and the patient’s rights under the health insurance portability and accountability act of 1996 (hipaa). Please complete all sections of this hipaa release form.

FREE 8+ Sample Hipaa Release Forms in PDF MS Word

Free Printable Hipaa Authorization Form

Free Medical Records Release Authorization Forms (HIPAA)

Hipaa Fillable Form Pdf Printable Forms Free Online

HIPAA Consent Form Fill Out, Sign Online and Download PDF

FREE 11+ Sample HIPAA Forms in PDF MS Word

Printable HIPAA Forms Complete with ease airSlate SignNow
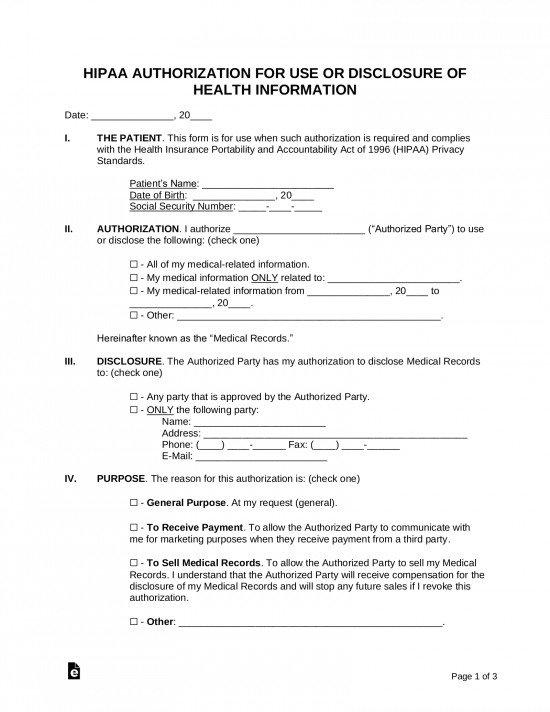
Free Medical Records Release Authorization Form (Waiver) HIPAA PDF

Printable HIPAA 20022025 Form Fill Out and Sign Printable PDF

Printable HIPAA Consent Form Template Digital Download Editable Medical
Free Immediate Download Of Medical Relasese Form Pdf.
This form is for use when such authorization is required and complies with the health insurance portability and accountability act of 1996 (hipaa) privacy standards. Please complete all sections of this hipaa release form. Powers granted under a medical release can be revoked or reassigned at any time. It also allows the added option for healthcare providers to share information.
I Understand That I Have Certain Rights To Privacy Regarding My Protected Health Information.
I understand that by signing this consent i authorize you to use and disclose my protected health information to carry out: These rights are given to me under the health insurance portability and accountability act of 1996 (hipaa). To fill out a hipaa release form, a patient must choose the appropriate document. How to fill out a hipaa release form.
The Medical Record Information Release (Hipaa) Form Allows Patients To Give Authorization To A 3Rd Party And Access Their Health Records.
In the event the health information described below includes any of these types of information, and i initial the line on the box in item 8(a), i specifically authorize release of such information to the person(s) indicated in item 7. The form must allow them to request their personal health information (phi) or grant a third party permission to release it. Check the applicable box to indicate to whom you authorize the release of your medical info. If any sections are left blank, this form will be invalid and it will not be possible for your health information to be shared as requested.
Direct Free Access To Pdf Of Hipaa Release.
Medical release forms include details about the information authorized for disclosure, its purpose, and the patient’s rights under the health insurance portability and accountability act of 1996 (hipaa).