Free Printable Hipaa Form
Free Printable Hipaa Form - I expressly request that the designated record custodian of all covered entities under hipaa identified above disclose full and complete protected medical information including the following: Understand how a hipaa release form works when disclosing confidential medical information. Authorize and request the disclosure of all protected information for the purpose of review and evaluation in connection with a legal claim. Download a free template and example here. This form is for use when such authorization is required and complies with the health insurance portability and accountability act of 1996 (hipaa) privacy standards. Please complete all sections of this hipaa release form. Direct free access to pdf of hipaa release. How to fill out a hipaa release form. Hipaa forms are used in accordance with the health insurance portability and accountability act (hipaa) of 1996. To fill out a hipaa release form, a patient must choose the appropriate document.

Free Printable Hipaa Authorization Form

Hipaa Release Of Information Form Fill Online, Printable, Fillable

FREE 11+ HIPAA Release Form Samples in PDF MS Word

HIPAA Consent Form Fill Out, Sign Online and Download PDF

Printable Hipaa Release Form

Patient Free Printable Hipaa Forms
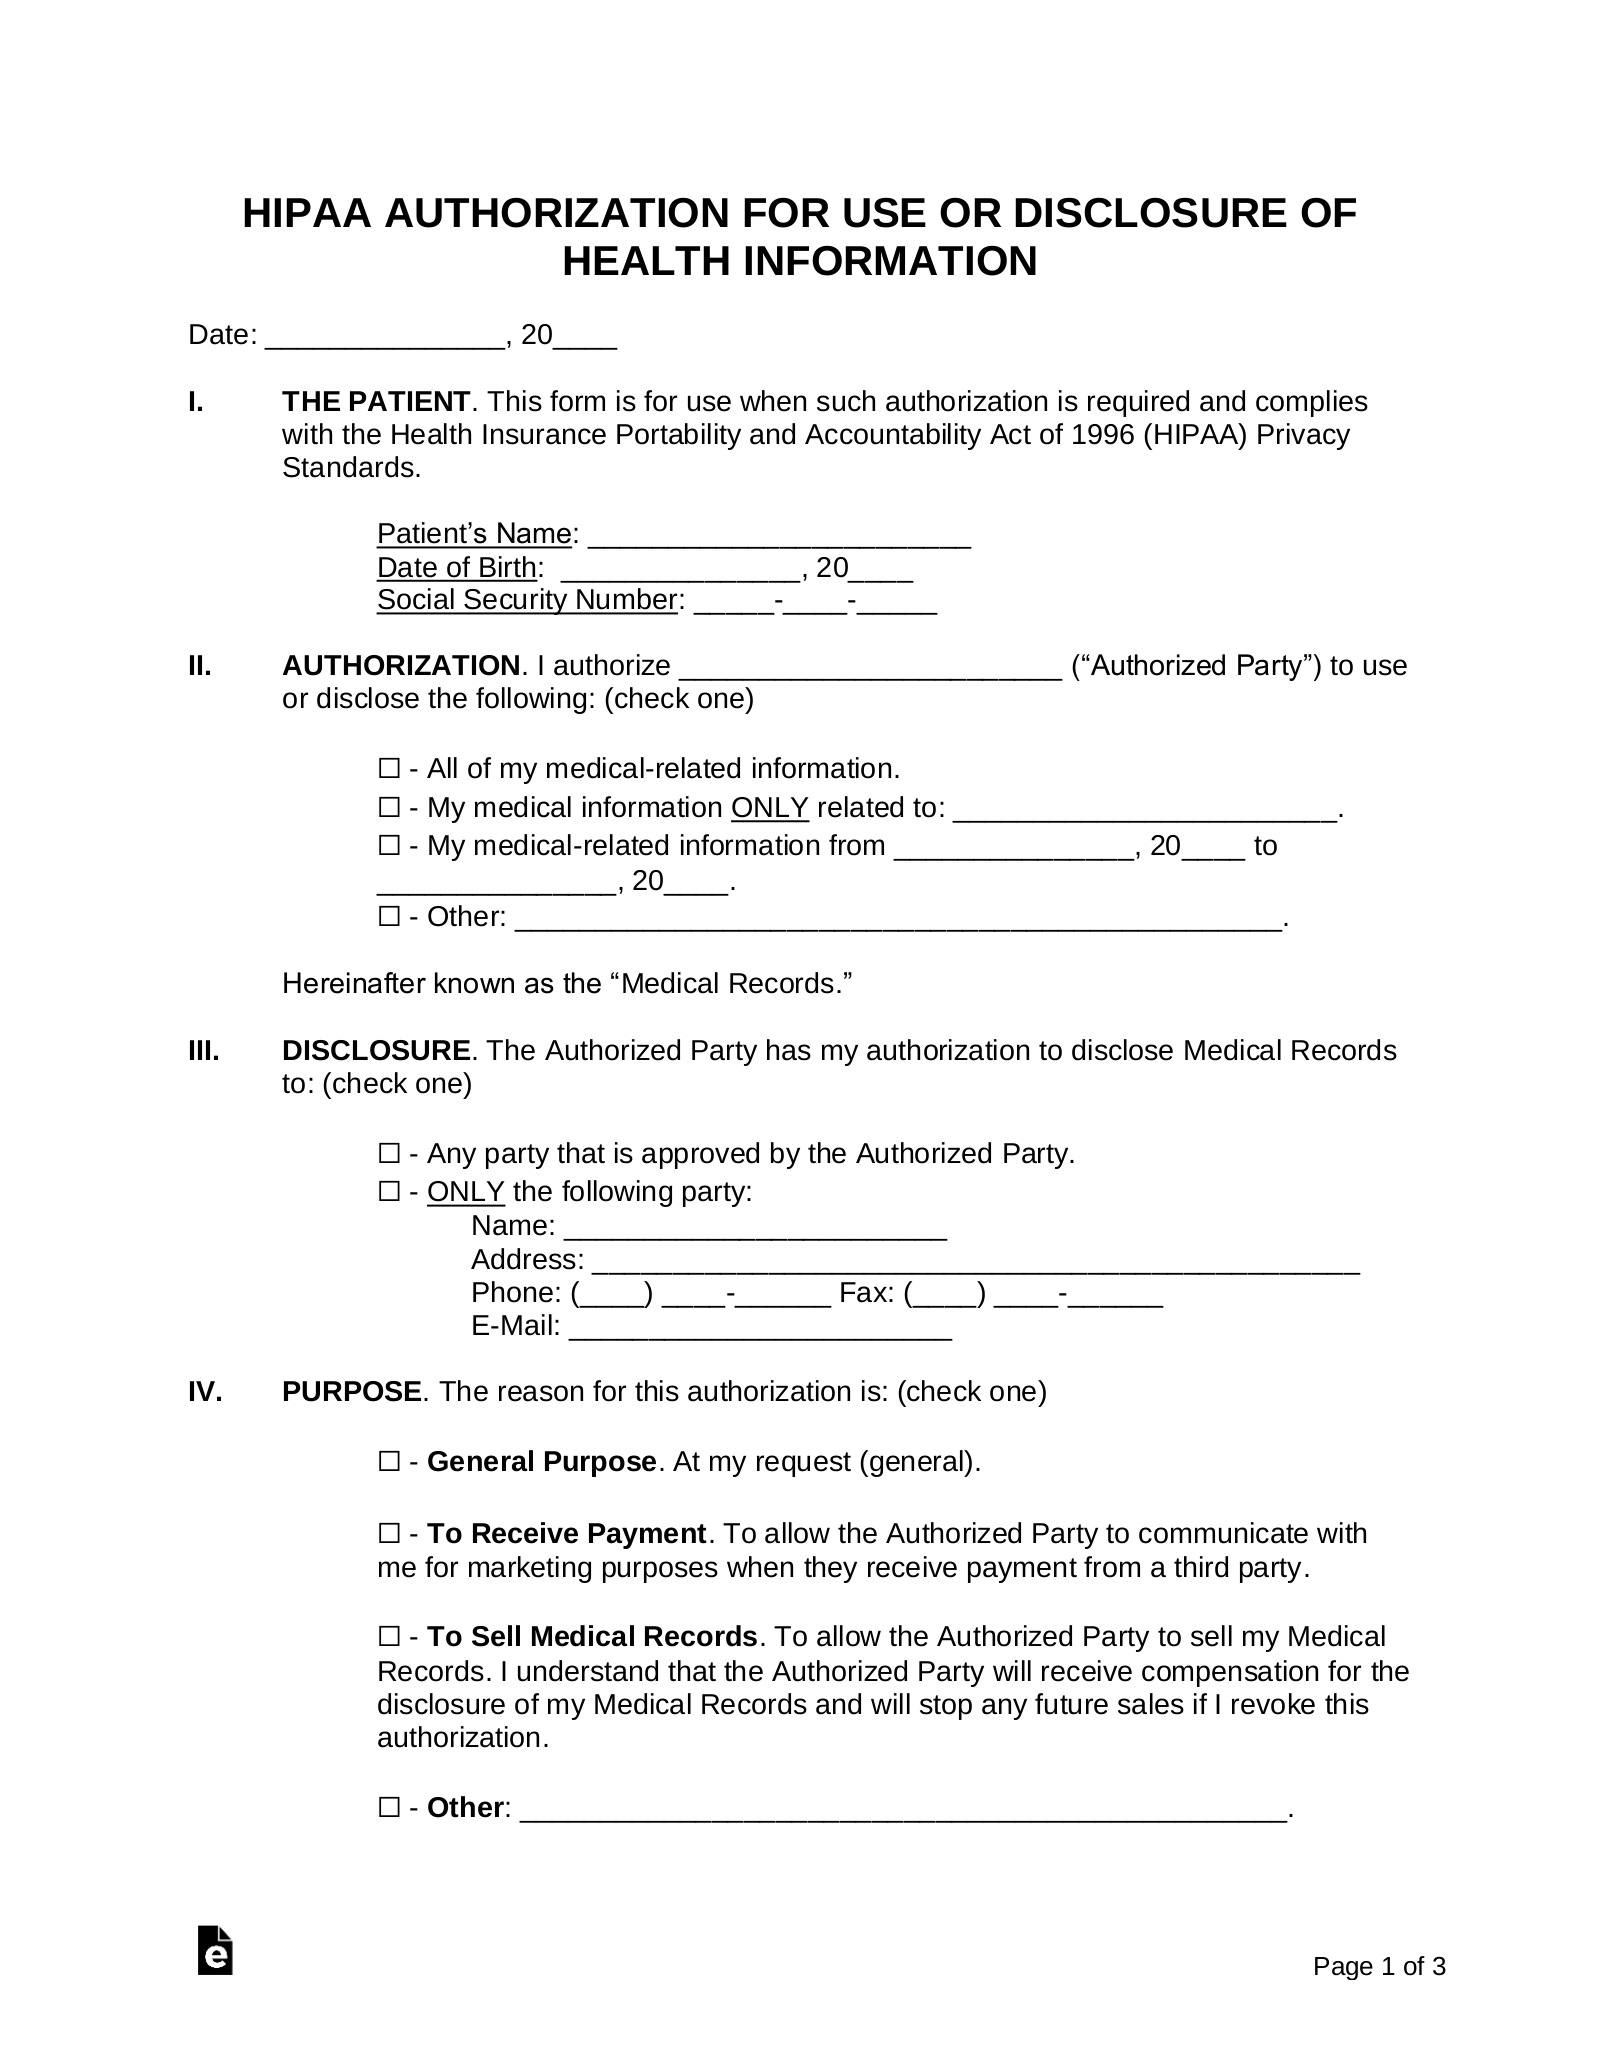
Printable Hipaa Forms Master of Documents

Printable Hipaa Authorization Form Master of Documents
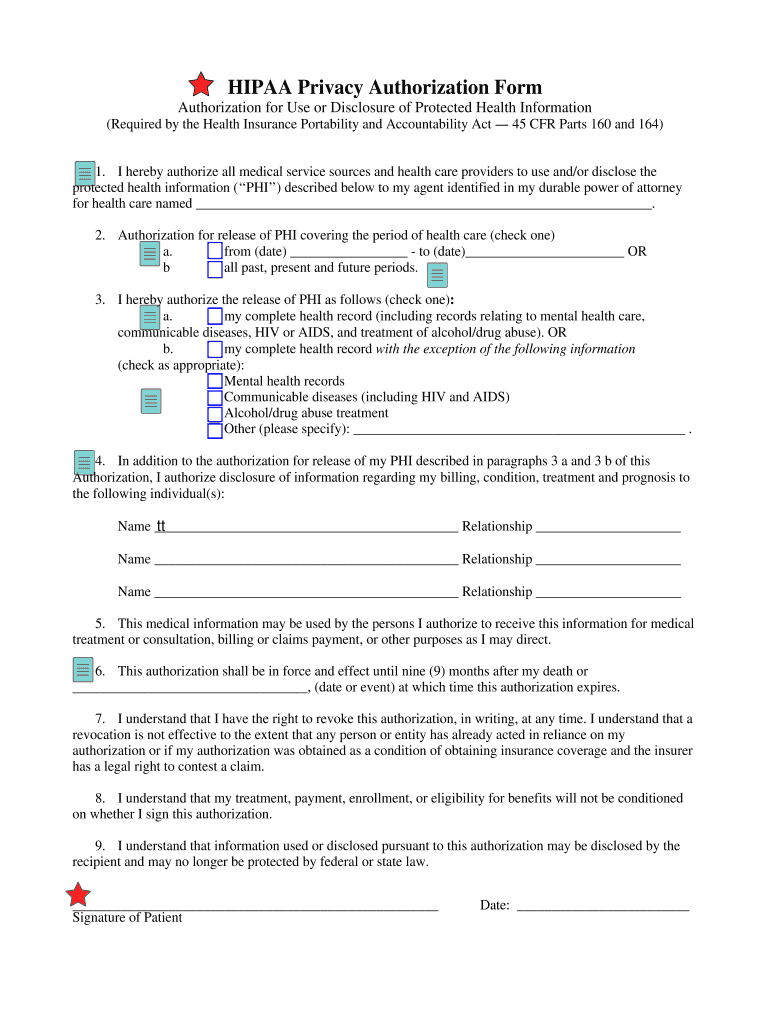
Printable Hipaa Forms Fill Online, Printable, Fillable, Blank pdfFiller

Free Printable Hipaa Form
This Form Is For Use When Such Authorization Is Required And Complies With The Health Insurance Portability And Accountability Act Of 1996 (Hipaa) Privacy Standards.
Hipaa privacy authorization form **authorization for use or disclosure of protected health information (required by the health insurance portability and accountability act, 45 c.f.r. Download a free template and example here. I expressly request that the designated record custodian of all covered entities under hipaa identified above disclose full and complete protected medical information including the following: Please complete all sections of this hipaa release form.
Free Immediate Download Of Medical Relasese Form Pdf.
Understand how a hipaa release form works when disclosing confidential medical information. Authorize and request the disclosure of all protected information for the purpose of review and evaluation in connection with a legal claim. If any sections are left blank, this form will be invalid and it will not be possible for your health information to be shared as requested. The form must allow them to request their personal health information (phi) or grant a third party permission to release it.
Their Purpose Is To Safeguard Protected Health Information (Phi) When Accessing And Sharing It With Authorized Third Parties.
Direct free access to pdf of hipaa release. To fill out a hipaa release form, a patient must choose the appropriate document. Authorization** i authorize _____ (healthcare provider) to use and disclose the protected health information Hipaa forms are used in accordance with the health insurance portability and accountability act (hipaa) of 1996.
Parts 160 And 164)** **1.
How to fill out a hipaa release form.