Cms1490S Printable Form
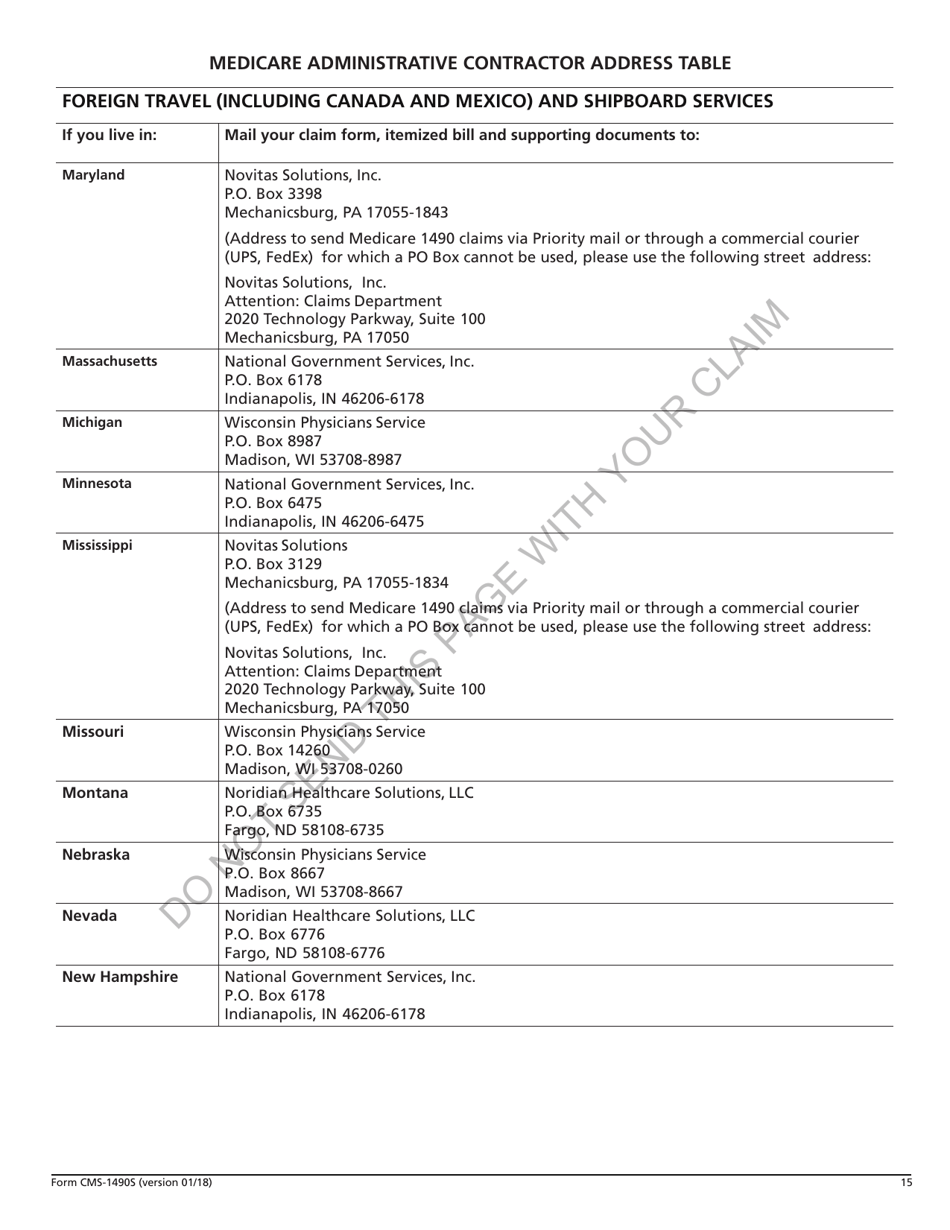
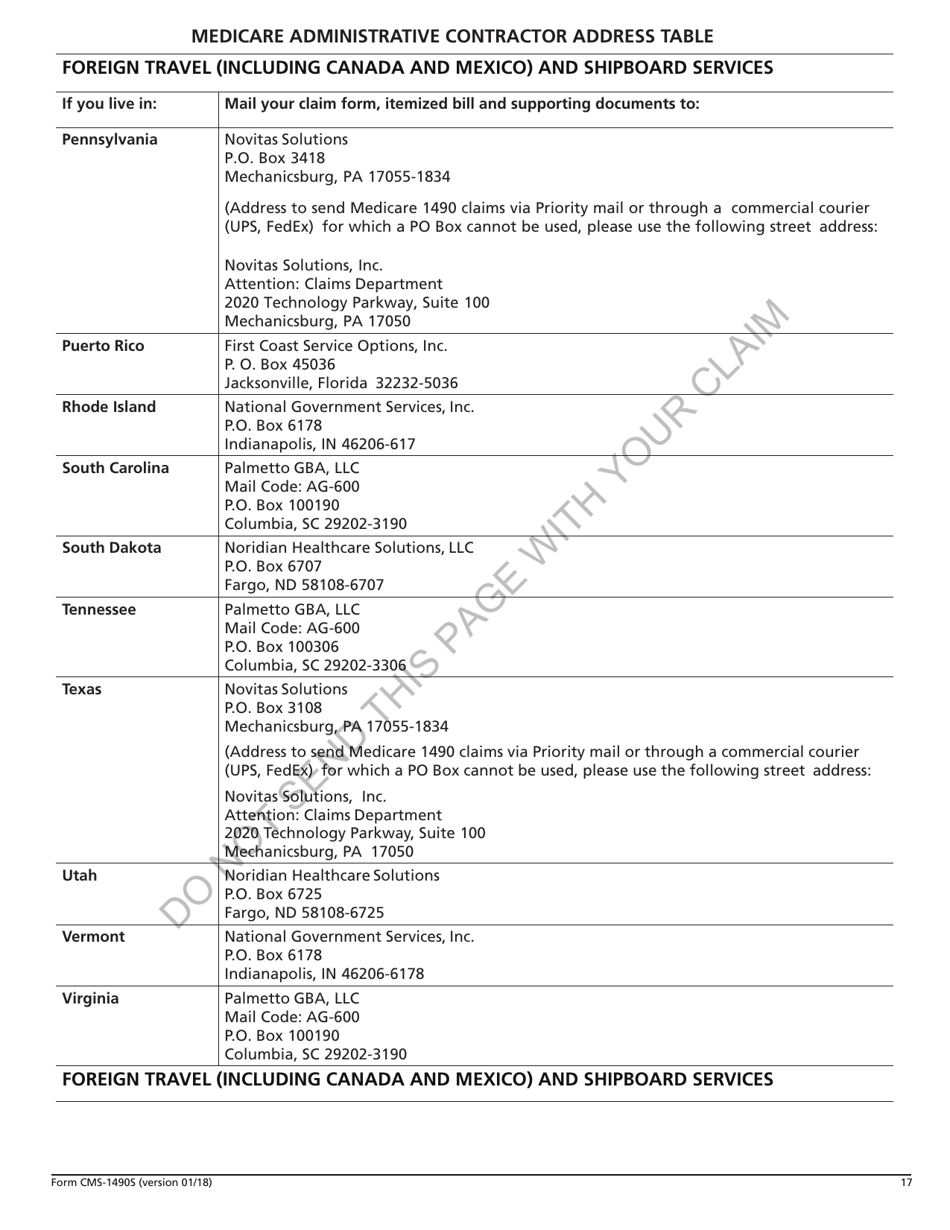
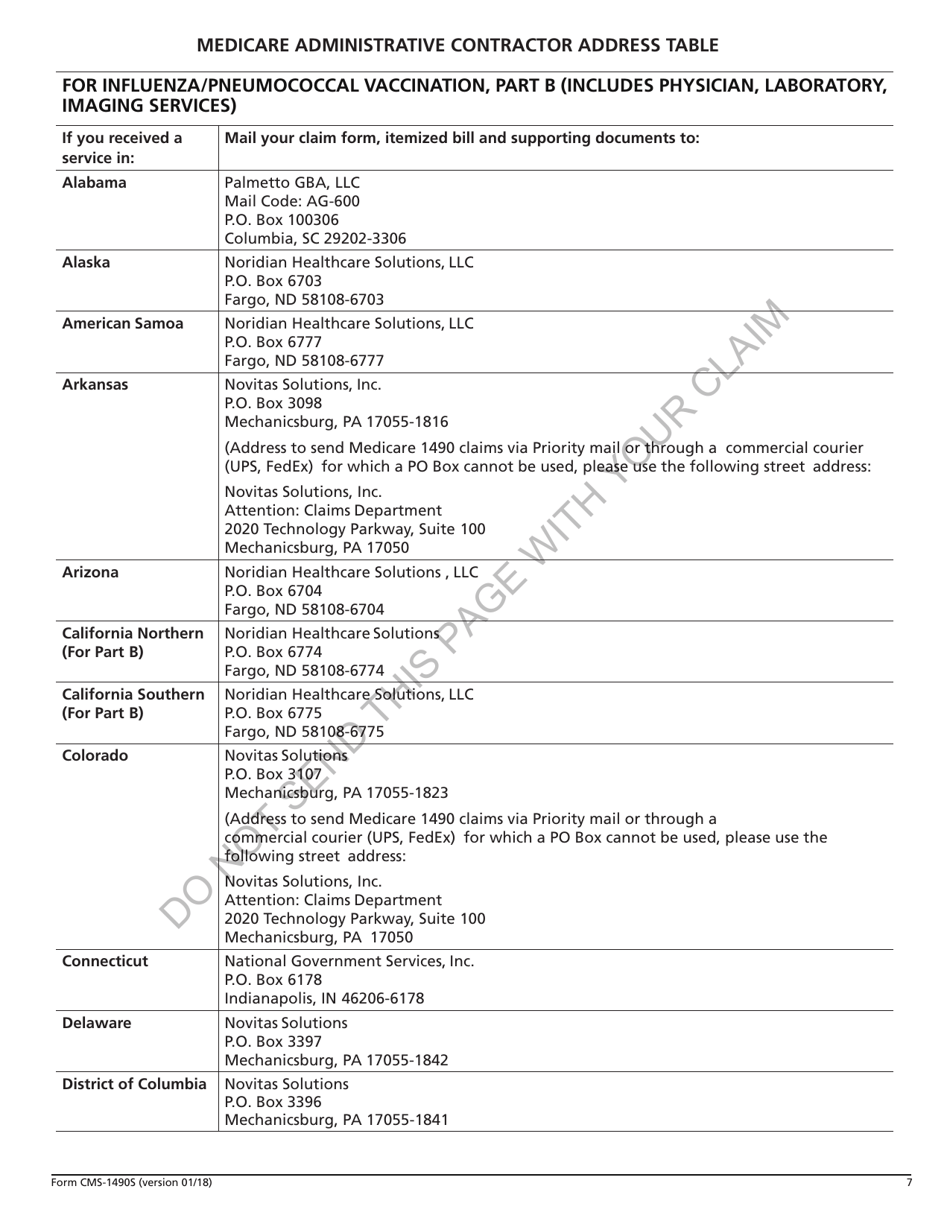
Cms1490S Printable Form - Each of the pdf files in the links below contains a cms1490s form along with instructions pertinent to the situation in which the medical care/supplies were provided. Thank you for your recent request for the patient’s request for medical payment form (cms1490s). Print your name shown on your medicare card (last name, first name, middle name). What do i submit with the claim? Print your name shown on your medicare card (last name, first name, middle name). Please send the completed claim form, your itemized bill, and any supporting documents to the appropriate medicare contractor and explain in detail your reason for submitting the claim. This form is for sharp health plan medicare members to request medical payment for: Medicare can’t pay its share if the submission doesn’t happen within 12 months. Patient’s request for medical payment. Follow the instructions for the type of claim you're filing (listed above under how do i file a claim?).
Form CMS1490S Fill Out, Sign Online and Download Fillable PDF
Formulario CMS1490S Download Printable PDF or Fill Online Peticion Del

Form CMS1490S Fill Out, Sign Online and Download Fillable PDF
Fill Free Fillable Cigna Medicare Providers Pdf Forms 186
medicare cms 1490s claim form

Formulario CMS1490S Download Printable PDF or Fill Online Peticion Del
Form CMS1490S Fill Out, Sign Online and Download Fillable PDF
Form CMS1490S Fill Out, Sign Online and Download Fillable PDF

Form CMS1490S Fill Out, Sign Online and Download Fillable PDF
Form Cms1490s (Sc) Patient'S Request For Medical Payment printable
Web Medicare Part C Member Reimbursement Request Form.
Edit on any devicecancel anytimetrusted by millionsfree mobile app Patient’s request for medical payment. Medicare can’t pay its share if the submission doesn’t happen within 12 months. Please read the attached instructions prior to submitting a claim to.
Print Out The Form And Instructions That Apply To Your Situation (Like For Services You Got On A Cruise Ship Or During Other Foreign Travel).
Filing a claim when you get services and/or supplies (if your provider doesn’t file it). Thank you for your recent request for the patient’s request for medical payment form (cms1490s). They must also attach any bill ( s) they received from providers/suppliers. Hospital that can treat your medical condition, regardless of whether an emergency exists.
Please Read The Attached Instructions Prior To Submitting A Claim.
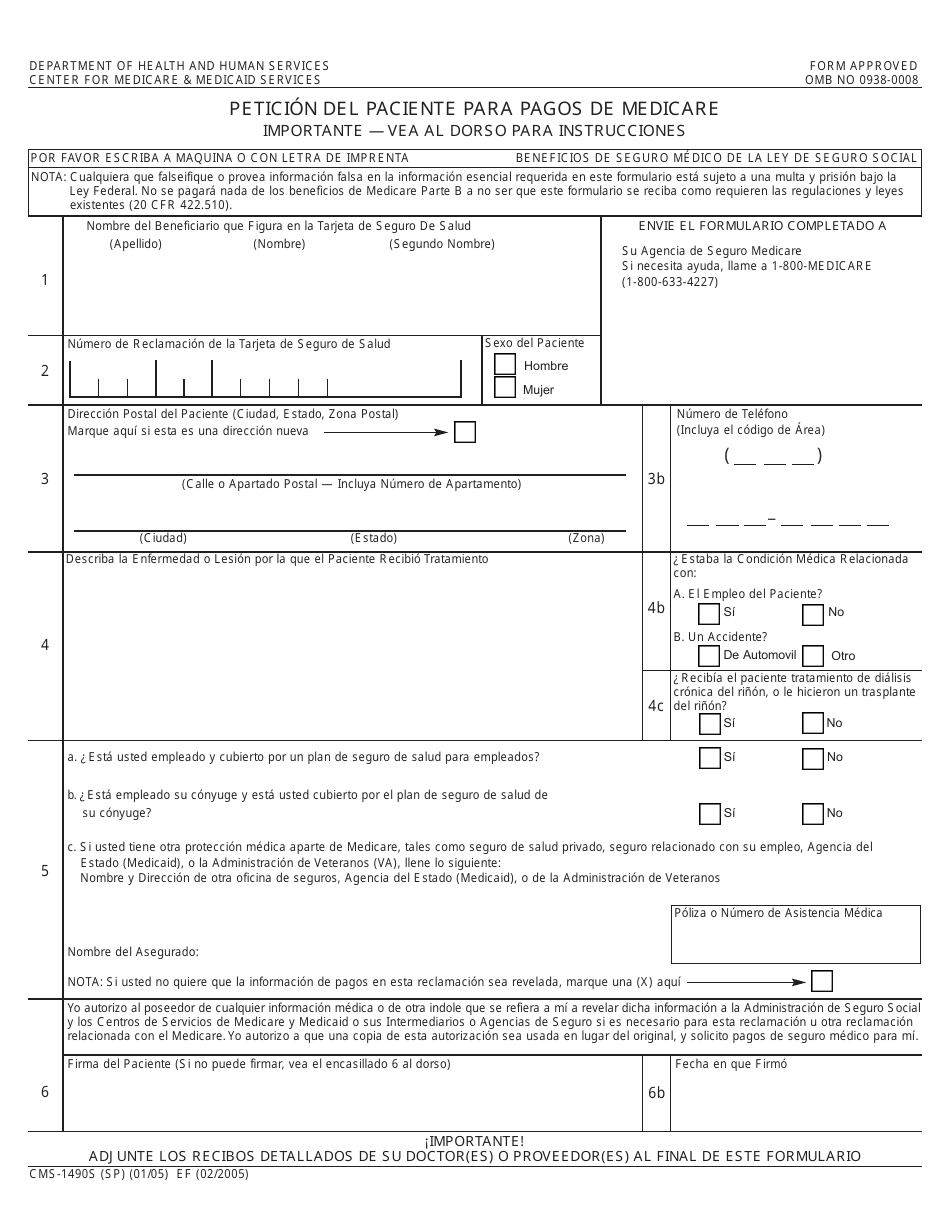
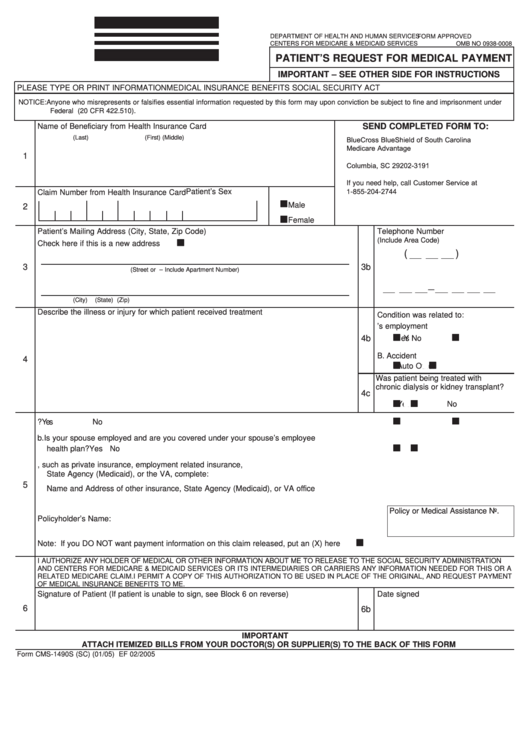
Department of health and human services. Department of health and human services centers for medicare & medicaid services. Print your health insurance claim number including the letter at the end exactly as it is shown on your medicare card. Patient’s request for medical payment.
Make Sure It’s Filed No Later Than 1 Full Calendar Year After The Date Of Service.
Form approved centers for medicare & medicaid services. Print your health insurance claim number including the letter at the end exactly as it is shown on your medicare card. Send the form to the company that processes your medicare claims. Check the appropriate box for the patient’s sex.